
Sleep & Circadian Disorders
Restless Legs Syndrome
Restless legs syndrome, or RLS, is a sleep-related movement disorder that causes a strong urge to move the legs, usually with uncomfortable sensations that are worse during rest and in the evening or night. Moving, stretching, or walking often brings temporary relief.
RLS is real, common, and often treatable. Because symptoms can disrupt sleep and negatively affect daytime function, evaluation can help identify next steps and reduce the burden across the whole 24 hours.
Overview
- Restless legs syndrome causes an urge to move the legs, often with sensations described as crawling, pulling, aching, tingling, or burning
- Symptoms usually begin or worsen when a person is resting, sitting, or lying down, and are usually worse in the evening/night
- Movement often improves symptoms for a short time
- RLS can make it difficult to fall asleep, stay asleep, travel, sit through meetings, relax in the evening, or share a bed comfortably
- Low iron levels, pregnancy, kidney disease, some medications, untreated sleep apnea, and family history may contribute to RLS
- Treatment may include checking iron status, addressing triggers, treating related conditions, behavioral strategies, and medication when appropriate
About restless legs syndrome
Restless legs syndrome (RLS), also known as Willis-Ekbom disease, is diagnosed primarily from a person’s symptoms. There is no single test that confirms RLS. Instead, healthcare professionals look for characteristic symptom patterns and rule out other possible explanations, such as leg cramps, nerve pain, or arthritis.
RLS can affect people of any age, although it becomes more common with age and is reported more often in women. Because the sensations can be difficult to describe or mistaken for other conditions, some people live with symptoms for years before receiving a diagnosis.
Many people with RLS also experience periodic limb movements during sleep (PLMS), which involve repeated, involuntary leg movements while asleep. However, PLMS and RLS are not the same. PLMS can be identified during a sleep study, while RLS is generally diagnosed based on symptoms experienced while awake.

Signs and symptoms
Restless legs syndrome (RLS) is often most noticeable in the evening or at night, when symptoms can make it difficult to relax or fall asleep. However, the effects can extend throughout the day, particularly when poor sleep causes fatigue or interferes with daily activities.
Likewise, actions people take throughout the day impact sleep – diet, exercise, alcohol, caffeine, medications, and stress can all affect how people sleep. A whole-24-hours approach looks at how people can promote health and well-being during both the day and the night, so that people can find opportunities to thrive and be well.
Nighttime and rest-related symptoms
Common evening and nighttime RLS symptoms include:
- A strong urge to move the legs
- Uncomfortable sensations deep in the legs
- People describe crawling, pulling, itching, tingling, aches, throbbing, or burning
- Symptoms that begin or worsen when sitting, lying down, or trying to sleep
- Temporary relief with walking, stretching, rubbing, or moving the legs
- Symptoms that are strongest in the evening or at night
- Difficulty falling asleep or returning to sleep after waking due to the urge to move
- Sometimes affects arms and other body regions if severe
Daytime symptoms
RLS can affect the daytime, especially when it disrupts sleep or makes sitting still difficult. People may notice:
- Fatigue or sleepiness
- Reduced focus or mental clarity
- Irritability, low mood, or anxiety about bedtime
- Trouble sitting for long periods due to discomfort
- Reduced quality of life
- Bed partner disruption, especially if leg movements occur in bed
Symptoms can range from mild and occasional to severe and frequent. Their intensity may also change over time.
Screening and diagnosis
Restless legs syndrome (RLS) is usually diagnosed based on a person’s symptoms and medical history. A healthcare professional will review when symptoms occur, what triggers them, and whether movement provides relief. They will also consider other conditions that could explain the discomfort.
Evaluation may include:
- Symptom history, including timing, triggers, and relief with movement
- Review of medications and supplements
- Medical history, including kidney disease, pregnancy, neuropathy, anemia, and sleep disorders
- Blood tests to assess iron status, often including ferritin and transferrin saturation
- Screening for other sleep disorders, including obstructive sleep apnea
- Sleep study when another sleep disorder is suspected, or when periodic limb movement disorder needs evaluation
When to talk with a healthcare professional
A person does not need to know the name or exact nature of a condition before asking for help. If a person experiences any of the symptoms above, it is appropriate to discuss them with a healthcare professional.
Red Flag: Seek urgent medical care if symptoms or sleep loss are affecting a person’s ability to drive or work safely, or is causing severe distress or thoughts of self-harm.
What to bring to a doctor’s visit
A primary care physician is a good place to start for a sleep disorder evaluation. They can conduct preliminary screenings and recommend next steps for diagnosis. It can be helpful to bring information to an initial visit: try using WSCN’s Preparing to meet your new healthcare provider checklist.
Causes, risk factors, and health implications
Causes and Risk Factors
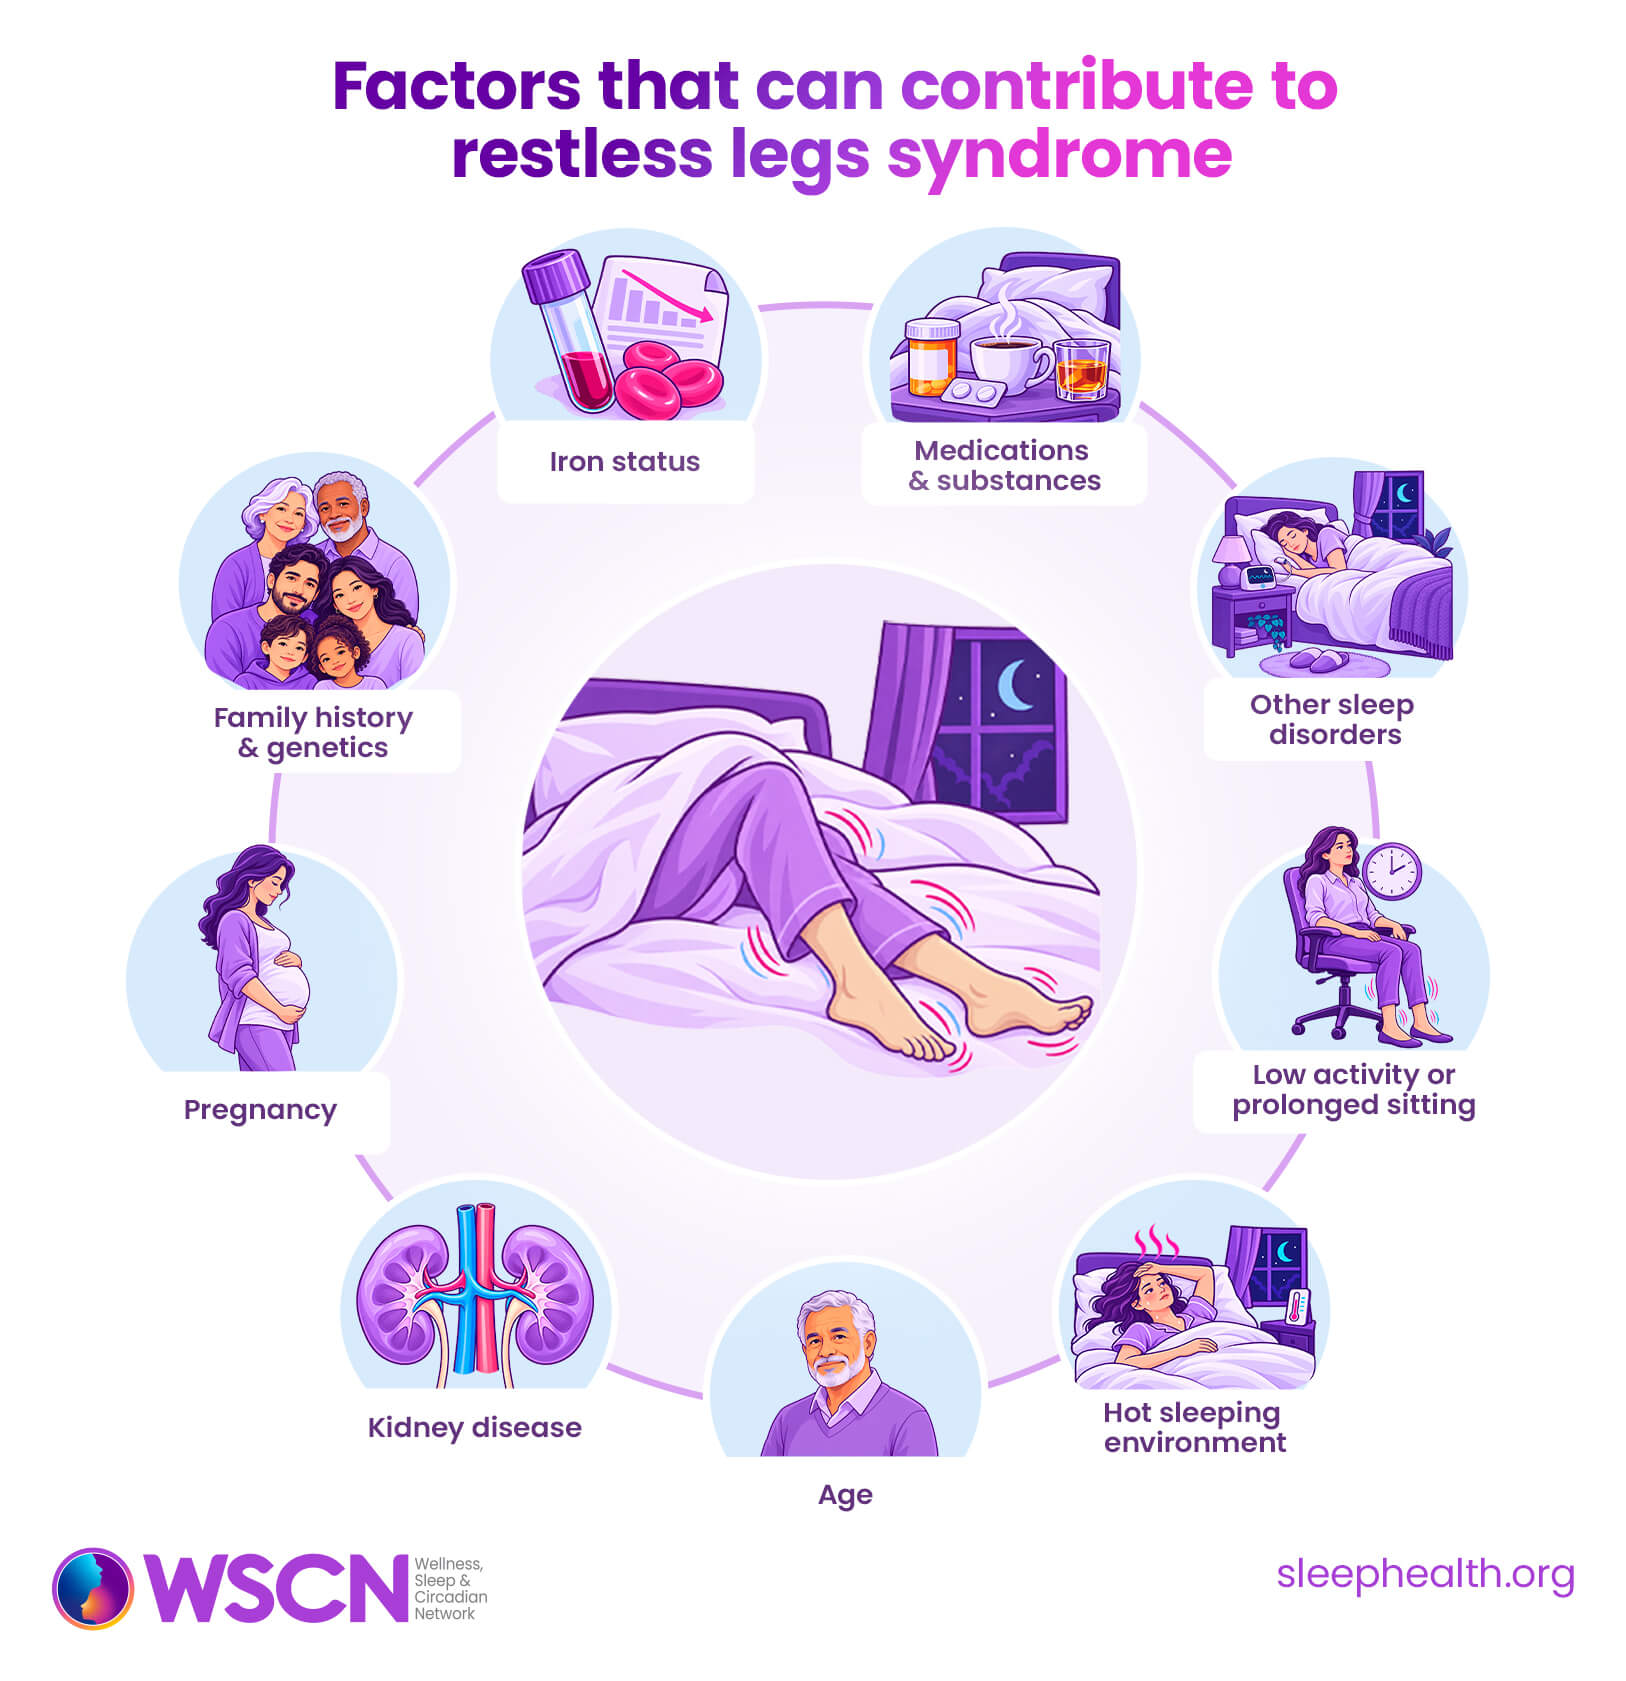
RLS can have more than one contributing cause, and for many people the cause is not fully clear. Common risk factors and contributors include:
- Iron status: Low or low-normal iron stores can contribute to symptoms, even when a person is not anemic.
- Family history and genetics: RLS can run in families, especially when symptoms begin earlier in life.
- Age: RLS becomes more common with advancing age.
- Pregnancy: Symptoms can appear or worsen during pregnancy, especially later pregnancy.
- Kidney disease: RLS is more common in people with chronic kidney disease and end-stage kidney disease.
- Medications and substances: Some medications may worsen symptoms, including certain antihistamines, antidepressants, antinausea medicines, and dopamine-blocking medications. Alcohol and caffeine may worsen symptoms for some people.
- Other sleep disorders: Untreated obstructive sleep apnea or poor sleep quality may worsen symptoms or make them harder to manage.
- Low activity or prolonged sitting: Sitting still for long periods can trigger RLS symptoms, particularly during travel or in the evening. This is a symptom trigger rather than a cause of the disorder.
- Hot sleeping environment: Some people report worse RLS symptoms in warm sleeping conditions, although the evidence is limited and individual responses vary.
Long-term health implications
Persistent restless legs syndrome (RLS) can affect more than sleep. Ongoing symptoms and disrupted sleep can influence physical and mental health, as well as quality of life.
- Sleep and mental health: Chronic sleep disruption can contribute to fatigue, anxiety, depressive symptoms, and reduced emotional wellbeing.
- Cardiovascular health: Some studies have linked RLS with high blood pressure and cardiovascular disease, although it remains unclear whether RLS directly contributes to these conditions.
- Daily functioning and safety: Poor sleep and ongoing discomfort can affect concentration, work performance, and the ability to manage everyday activities.
- Relationships and quality of life: RLS can interfere with evening activities, travel, and social life. Symptoms may also disrupt a bed partner’s sleep.
Recognizing and treating RLS can help reduce symptoms, improve sleep, and support better health and wellbeing across all 24 hours.
Treatment and management
Treatment for restless legs syndrome (RLS) focuses on reducing symptoms, improving sleep, and supporting daily functioning. The best approach depends on symptom severity, underlying health conditions, and individual needs. Treatment options may include:
- Checking iron levels: Low iron stores can contribute to RLS, even without anemia. Oral or intravenous iron may be recommended based on blood test results and medical assessment.
- Medications: Gabapentin, pregabalin, and gabapentin enacarbil are recommended treatments for many adults with RLS. Dopamine agonists, once widely used, are no longer routinely recommended because long-term use can cause augmentation, in which symptoms become more severe or begin earlier in the day.
- Non-medication devices: Specialized devices that provide gentle stimulation may help reduce symptoms in some people.
- Managing triggers and related conditions: Reviewing medications and reducing substances that worsen symptoms can help. Treating conditions such as sleep apnea or kidney disease may also improve symptom management.
- Healthy daily routines: Regular physical activity, consistent sleep schedules, and movement breaks during prolonged sitting may help reduce discomfort.
A healthcare professional can help identify the most appropriate treatment and monitor symptoms over time. Do not start iron supplements or change prescribed medications without medical guidance.
Research and what we are still learning
Researchers continue to investigate the underlying causes of restless legs syndrome (RLS), including the roles of genetics and iron regulation in the brain. Understanding these processes may help explain why symptoms vary between individuals and lead to more targeted treatments.
Another focus is developing safer and more effective long-term treatments, particularly for people with severe or persistent symptoms. Studies are also exploring non-medication devices and how RLS affects cardiovascular health and quality of life.
Research into RLS during pregnancy and in people with kidney disease may help improve care for these groups.
Allen, R. P., Picchietti, D. L., Garcia-Borreguero, D., et al. (2014). Restless legs syndrome/Willis-Ekbom disease diagnostic criteria: Updated International Restless Legs Syndrome Study Group consensus criteria—History, rationale, description, and significance. Sleep Medicine, 15(8), 860–873. https://doi.org/10.1016/j.sleep.2014.03.025
Broström, A., Alimoradi, Z., Odzakovic, E., et al. (2024). Quality of life among patients with restless legs syndrome: A systematic review and meta-analysis. Journal of Clinical Neuroscience, 122, 80–91. https://doi.org/10.1016/j.jocn.2024.02.027
Didriksen, M., et al. (2024). Genome-wide meta-analyses of restless legs syndrome yield insights into genetic risk and biology. Nature Genetics, 56, 1487–1497. https://doi.org/10.1038/s41588-024-01763-1
Gottlieb, D. J., Somers, V. K., Punjabi, N. M., et al. (2017). Restless legs syndrome and cardiovascular disease. Sleep Medicine, 31, 98–106. https://doi.org/10.1016/j.sleep.2016.08.008
Silber, M. H., Buchfuhrer, M. J., Earley, C. J., et al. (2021). The management of restless legs syndrome: An updated algorithm. Mayo Clinic Proceedings, 96(7), 1921–1937. https://doi.org/10.1016/j.mayocp.2020.12.026
Winkelman, J. W., Berkowski, J. A., DelRosso, L. M., et al. (2025). Treatment of restless legs syndrome and periodic limb movement disorder: An American Academy of Sleep Medicine clinical practice guideline. Journal of Clinical Sleep Medicine, 21(1), 137–152. https://doi.org/10.5664/jcsm.11390
Oh SM, Son KL, Choi SJ, et al. The seasonal pattern of restless legs syndrome in a sample from the Korean Health Insurance Review and Assessment Service national database. J Clin Sleep Med. 2021 May 1;17(5):1051-1056. doi: 10.5664/jcsm.9136. PMID: 33570488; PMCID: PMC8320502. https://pubmed.ncbi.nlm.nih.gov/33570488/
Bogan RK, Roy A, Kram J, et al. Efficacy and safety of tonic motor activation (TOMAC) for medication-refractory restless legs syndrome: a randomized clinical trial. Sleep. 2023 Oct 11;46(10):zsad190. doi: 10.1093/sleep/zsad190. PMID: 37458698; PMCID: PMC10566236. https://pmc.ncbi.nlm.nih.gov/articles/PMC10566236/
This article is for educational purposes only and is not intended to replace professional medical advice, diagnosis, or treatment. Speak with a qualified healthcare professional about questions or concerns related to your sleep. Read full medical disclaimer
