
Sleep & Circadian Disorders

Bruxism

Bruxism means repeated jaw muscle activity that may include clenching, grinding, bracing, or thrusting the jaw. When it happens during sleep, it is called sleep bruxism. Many adults do not know it is happening until a bed partner hears tooth grinding or a dentist notices tooth wear.

Sleep bruxism is not always harmful, but it becomes more important to evaluate when it causes tooth damage, jaw pain, morning headaches, or disrupts sleep.

Overview

  • Sleep bruxism is repeated jaw muscle activity during sleep, often described as teeth grinding or clenching
  • It can cause tooth wear, jaw muscle pain, facial discomfort, morning headaches, or disturbed sleep
  • Some people have sleep bruxism without obvious symptoms or damage
  • Sleep bruxism may be associated with stress, genetics, certain medications, alcohol, caffeine, tobacco, and sleep-disordered breathing
  • Diagnosis often starts with dental and medical history; a sleep study may be used when another sleep disorder is suspected
  • Management focuses on protecting teeth, reducing pain, identifying contributors, and treating related sleep or health conditions

About bruxism

Bruxism involves repeated activity of the jaw muscles and can occur while a person is awake or asleep. Awake bruxism typically involves clenching or holding the jaw tense, often during periods of concentration or stress. Sleep bruxism occurs during sleep and may involve teeth grinding, clenching, or rhythmic jaw movements.

Sleep bruxism is classified as a sleep-related movement disorder. It often occurs alongside brief changes in sleep activity, known as arousals, when the brain temporarily shifts toward lighter sleep without fully waking. Most people are unaware these episodes are happening.

Sleep bruxism is relatively common, although estimates vary depending on how it is measured. Some people experience occasional jaw muscle activity without pain or dental damage, while others develop tooth wear, jaw discomfort, or other symptoms that affect their daily lives.

Sleep bruxism is not a “bad habit”. It involves complex interactions between the nervous system, sleep processes, and other factors. Understanding when it causes symptoms or damage can help determine whether treatment is needed.

Signs and symptoms

Sleep bruxism often goes unnoticed because it occurs during sleep. Some people only become aware of it when a bed partner hears teeth grinding or a dentist identifies signs of tooth wear.

Although sleep bruxism does not always cause symptoms, repeated jaw muscle activity may be associated with jaw discomfort, tooth sensitivity, or morning headaches. These symptoms can sometimes affect eating, speaking, concentration, and daily activities.

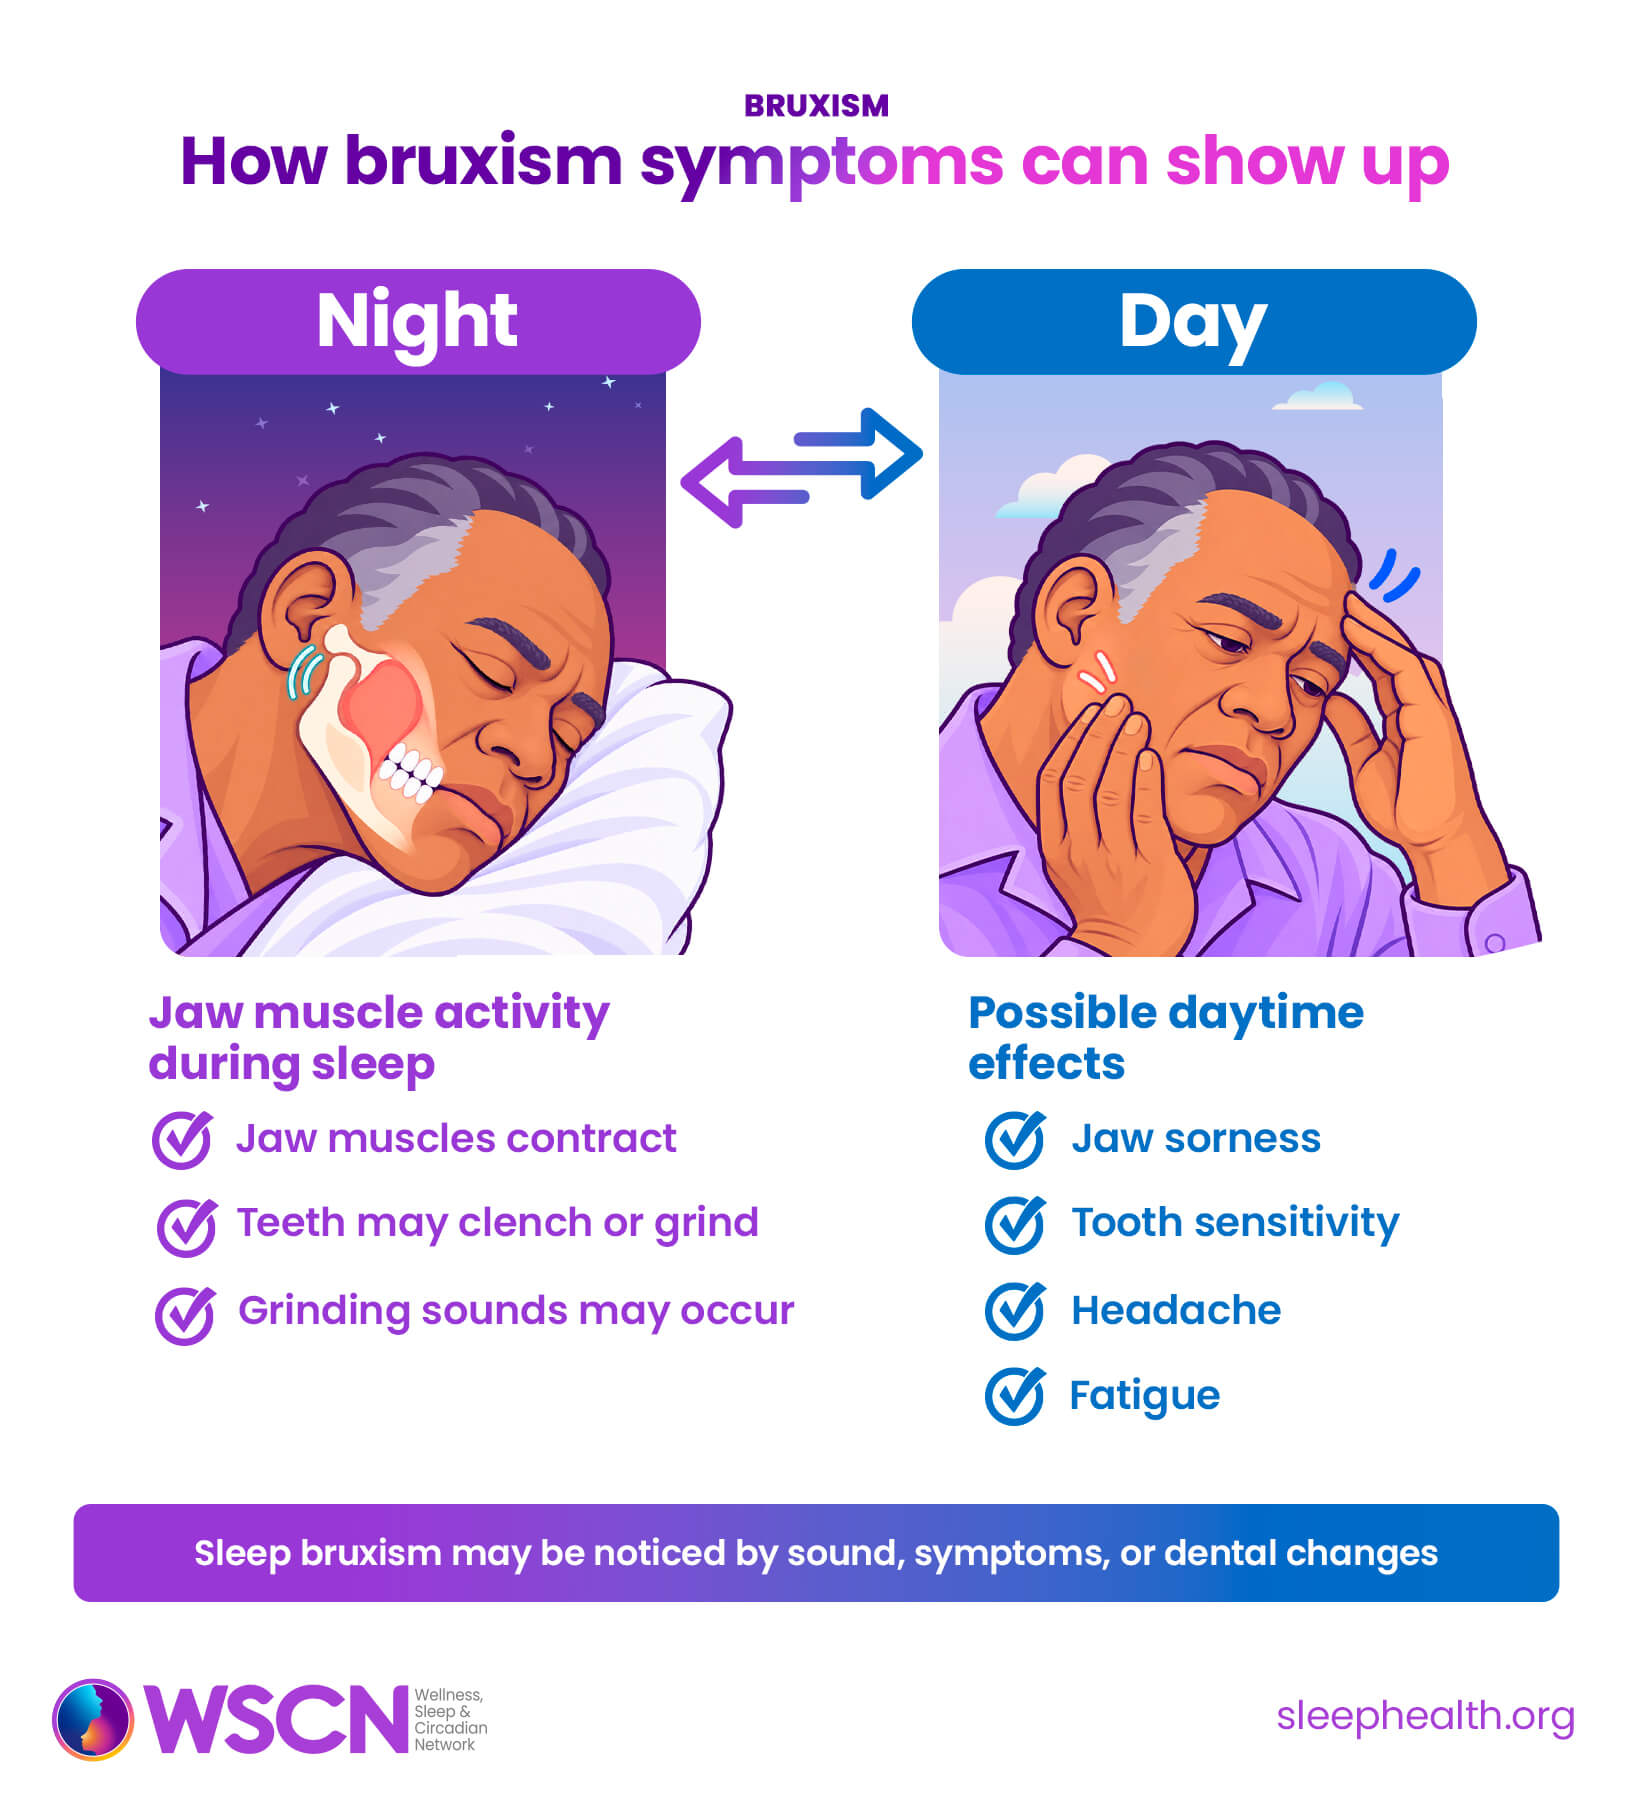
Nighttime signs

A person with sleep bruxism may notice or be told about:

  • Jaw movement, grinding or clenching sounds during sleep
  • Sleep disruption for a bed partner
  • Nighttime waking with a tight or tired jaw

Daytime symptoms

Sleep bruxism can also show up during the day as:

  • Jaw muscle soreness or stiffness, particularly in the morning
  • Difficulty opening the mouth fully or occasional jaw locking
  • Facial pain or discomfort around the ears
  • Morning headaches, particularly around the temples
  • Tooth sensitivity or pain
  • Chipped, flattened, fractured, or worn teeth or dental restorations
  • Fatigue or difficulty concentrating if sleep is disrupted

How symptoms can vary

Some people have noticeable tooth wear or grinding sounds without experiencing pain. Others report jaw discomfort or headaches without obvious dental damage.

Symptoms may change over time and sometimes become more noticeable during periods of stress, poor sleep, or medication changes. However, jaw pain, headaches, and tooth wear can have other causes and do not necessarily mean a person has active sleep bruxism.
Screening and diagnosis

Taking a whole-person 24-hour approach asks what happens before sleep, during sleep, and after waking. Tracking this pattern may show whether bruxism is linked with dental or medical conditions, daytime stressors, or other factors.

Evaluation may involve a dentist, primary care clinician, sleep medicine clinician, or oral medicine specialist. A clinician may ask about the following symptoms, so it can help to bring this information to an appointment:

  • Grinding sounds reported by a bed partner
  • Tooth wear, fractures, or dental sensitivity
  • Jaw pain, facial pain, headaches, or jaw locking
  • Sleep schedule and sleep quality
  • Snoring, gasping, witnessed breathing pauses, or daytime sleepiness
  • Alcohol, caffeine, nicotine, cannabis, or other substance use
  • Current medications, including antidepressants or stimulants
  • Stress, anxiety, trauma, pain, or other health conditions

A dentist may examine the teeth, gums, jaw muscles, bite, and temporomandibular joints. A sleep study is not usually needed to detect bruxism alone, but it may be recommended when obstructive sleep apnea, seizures, periodic limb movements, or another sleep disorder is suspected. Polysomnography with muscle and audio-video recording may be used to measure sleep bruxism in complex clinical cases.

When to visit a dentist or doctor

If a person experiences any of the symptoms listed above, or is concerned about their daytime or sleep health, it is recommended to make an appointment with a health professional. Seeking care promptly can help with receiving a clear diagnosis and treatment plan, and lead to improvements in wellbeing.

A dentist is often the first clinician to identify bruxism. A primary care clinician may also be involved in treatment and monitoring of non-dental contributors.

Questions to ask include:

  • Do my symptoms fit sleep bruxism?
  • Is there tooth damage that needs protection?
  • Could obstructive sleep apnea or another sleep disorder be involved?
  • Could medication, alcohol, caffeine, nicotine, or stress be contributing?
  • Would an oral appliance be appropriate for me?
  • What should I track before my next visit?

When to seek urgent medical attention

It is usually fine to wait a few weeks for an appointment to talk about sleep issues. 

Red flag: The following symptoms may be dangerous, and should receive prompt medical attention:

  • Sleep loss severe enough to cause drowsy driving or other safety risks
  • Bruxism that begins after dental procedures
  • Bruxism that begins after a medication or substance change
  • Daytime neurological symptoms or seizures
  • Sleep loss or pain causing new or worsening depression, hopelessness, or thoughts of self-harm

Risk factors and health implications

Causes and risk factors

Sleep bruxism does not have a single known cause. It appears to involve several factors related to brain activity, sleep patterns, genetics, and individual health. Some factors may increase the likelihood of teeth grinding or clenching during sleep, although their exact roles are not always clear.

Possible risk factors and contributing factors include:

  • Stress and emotional load: Stress, anxiety, and tension may worsen clenching or grinding for some adults.
  • Genetic tendency: Bruxism can run in families.
  • Sleep disruption: Fragmented sleep and brief arousals into lighter sleep may be linked with jaw muscle activity.
  • Sleep-disordered breathing: Sleep bruxism can occur in people with obstructive sleep apnea or snoring, although the relationship is complex.
  • Medications: Some medications, including certain antidepressants or stimulants, may contribute in some people.
  • Substances: Alcohol, caffeine, tobacco, and some recreational substances may increase risk or worsen symptoms.
  • Pain and jaw disorders: Temporomandibular disorder symptoms and jaw muscle pain can overlap with bruxism.
  • Schedule and lifestyle factors: Short sleep, irregular sleep timing, shift work, and high stress periods may affect symptom patterns.

Long-term health implications

Sleep bruxism does not always cause harm. However, frequent or forceful teeth grinding and jaw clenching may lead to dental problems, discomfort, and difficulties with everyday activities.

Possible long-term effects include:

  • Dental health: Repeated grinding or clenching may contribute to tooth wear, fractures, sensitivity, and damage to fillings, crowns, or other dental restorations.
  • Jaw pain and function: Some people experience persistent jaw muscle soreness, facial pain, headaches, or symptoms associated with temporomandibular disorders (TMD), which affect the jaw muscles and joints.
  • Sleep health: Grinding sounds may disturb a bed partner’s sleep. Sleep bruxism may also occur alongside other conditions that disrupt sleep, such as obstructive sleep apnea.
  • Emotional well-being: Ongoing pain, dental concerns, or poor sleep may contribute to stress, frustration, anxiety, or low mood.
  • Underlying health conditions: In some cases, bruxism may be associated with medication effects or other sleep and medical conditions that require evaluation.

Sleep bruxism itself is not known to directly cause cardiovascular or metabolic disease. However, associated conditions, particularly untreated obstructive sleep apnea, may carry broader health risks.

Identifying and managing problematic bruxism can help protect dental health, reduce discomfort, and improve daily well-being.

Treatment and Management

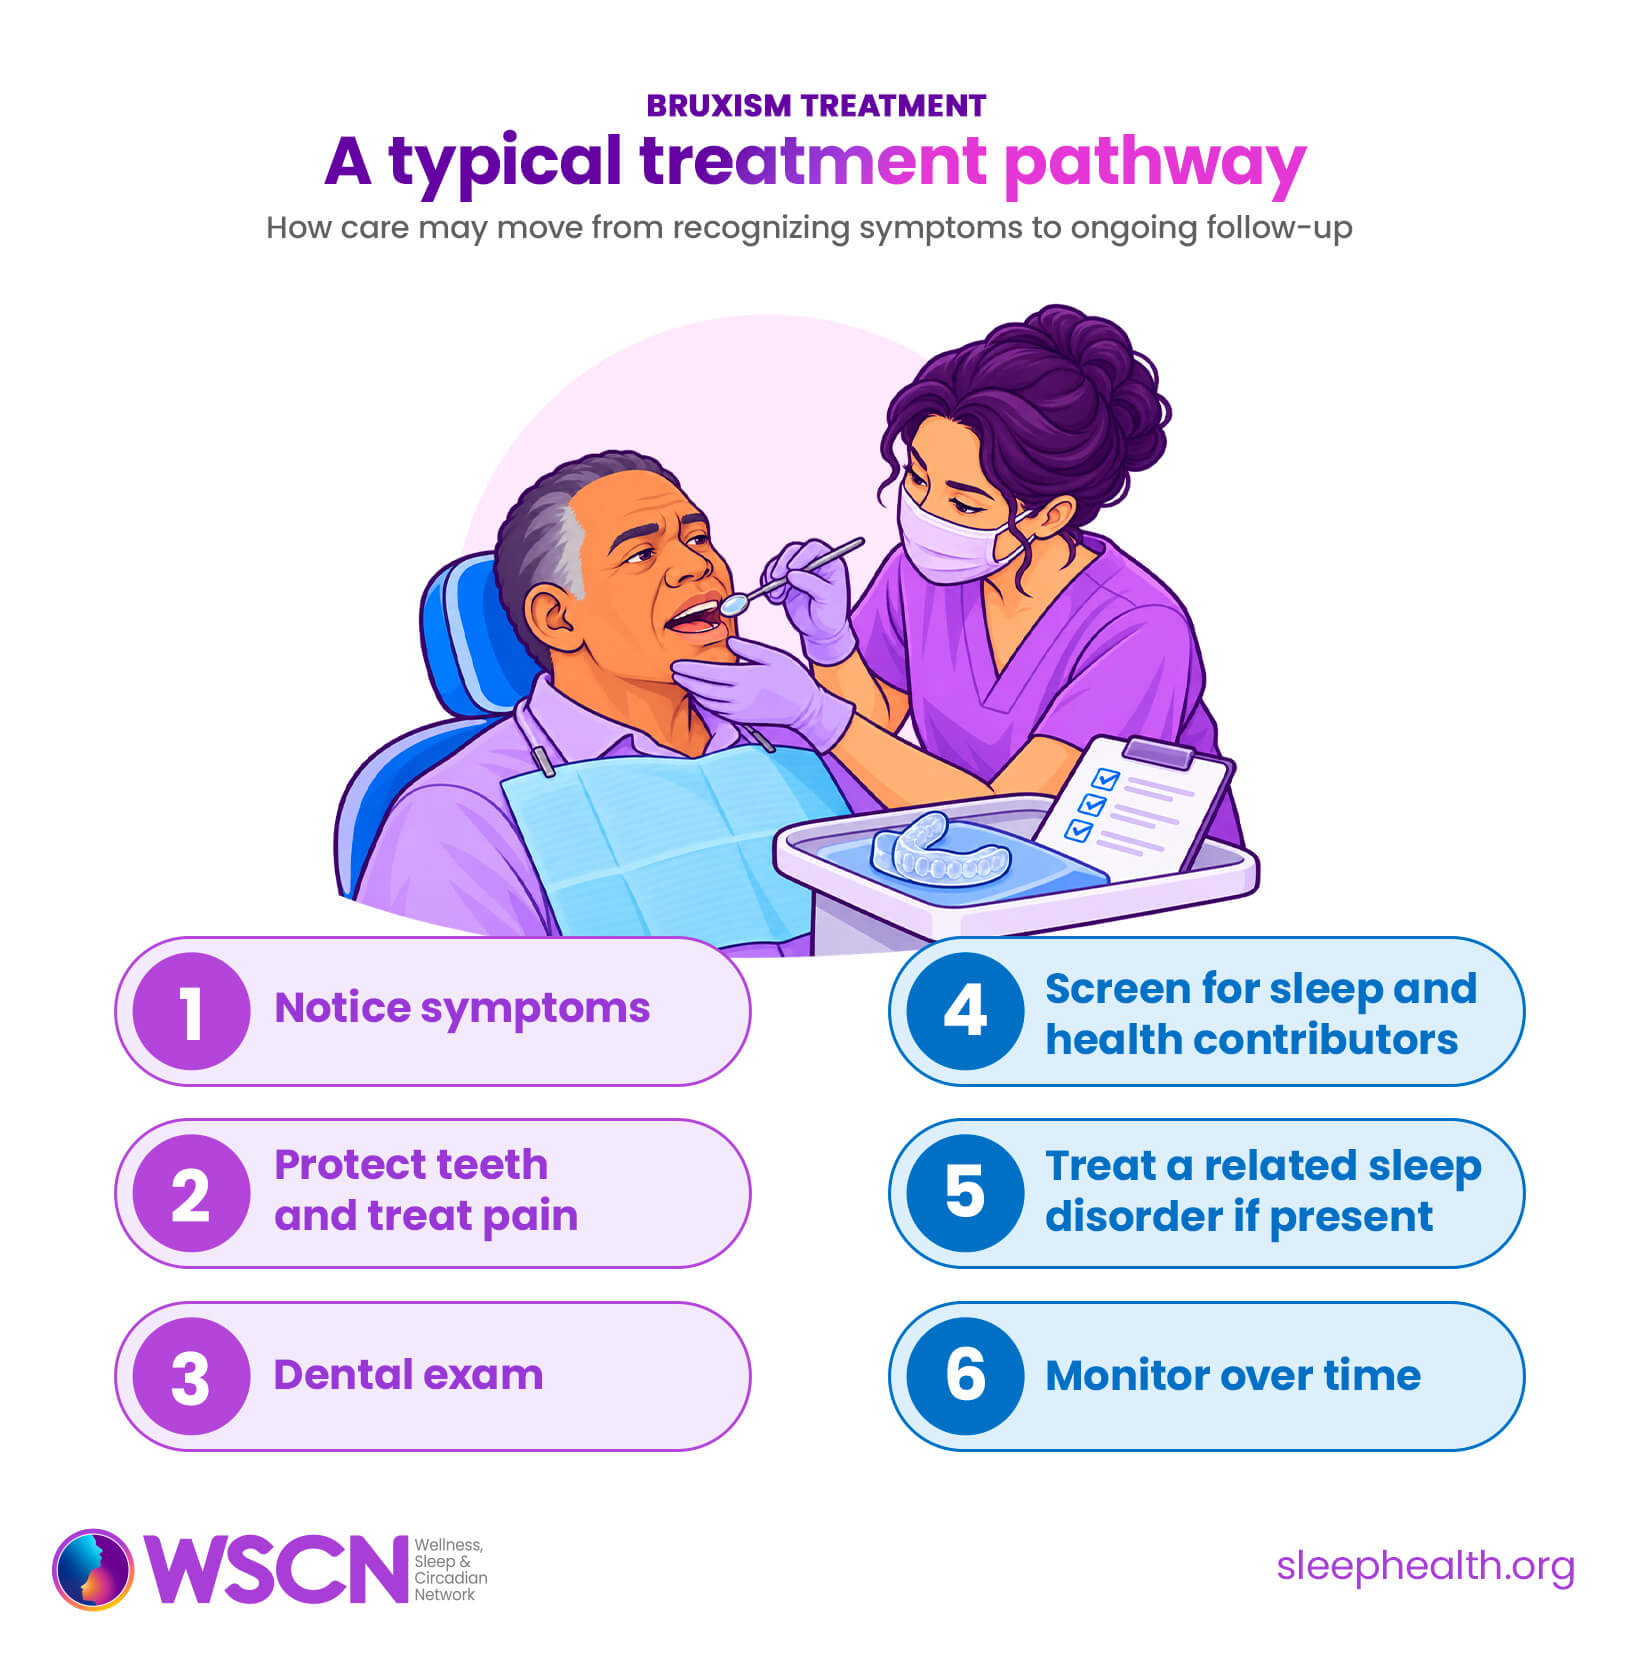
Treatment depends on symptoms, tooth damage, sleep quality, and contributing factors. Management usually focuses on protection, symptom relief, and identifying related conditions.

Dental protection

A dentist may recommend an oral appliance or splint to protect the teeth. These devices do not always stop the jaw muscle activity, but they can reduce tooth damage and may help with some symptoms. A custom-fitted device is often preferred when ongoing use is needed.

Pain and jaw muscle support

Management may include jaw relaxation strategies, avoiding gum chewing or prolonged jaw clenching, heat or cold as recommended, physical therapy, or care for temporomandibular disorder symptoms. Pain treatment should be individualized.

Sleep and 24-hour supports

While bruxism can cause disrupted sleep, insufficient or disrupted sleep can also contribute to bruxism. A whole-24-hours approach will prioritize supportive daytime behaviors and a healthy sleep routine to reduce bruxism symptoms. Helpful steps may include:

  • Keeping a consistent sleep-wake schedule
  • Allowing enough time for rest and sleep
  • Reducing alcohol close to bedtime
  • Reviewing caffeine and nicotine timing
  • Tracking whether symptoms follow short sleep, late nights, or shift changes
  • Treating insomnia, sleep apnea, or other sleep disorders when present

Stress management and behavioral approaches

Stress management does not mean the problem is “just stress.” It means the jaw and sleep systems may be sensitive to arousal. Relaxation training, biofeedback, cognitive behavioral therapy, or behavioral sleep medicine may help some adults, especially when bruxism overlaps with insomnia, anxiety, or daytime clenching.

Medication review

Medication is not usually the first treatment for sleep bruxism. However, if bruxism is severe, a doctor may prescribe a muscle relaxant to help ease nighttime symptoms.

If bruxism symptoms started or worsened after a medication change, a clinician can review options, since some medications can make bruxism worse. People should not stop prescribed medication without medical guidance.
Research and what we are still learning

Researchers are still working to clarify when sleep bruxism is a harmless sleep-related behavior and when it should be considered a disorder requiring treatment. A major challenge is measurement. Self-report, dental examination, portable electromyography, and sleep laboratory studies do not always identify the same patterns or findings.

Recent systematic reviews suggest that stabilization splints (mouth guards) may help reduce or manage sleep bruxism activity for some adults, but evidence is still limited and not all treatments have strong support. More research is needed on long-term outcomes, patient-centered measures, the relationship with obstructive sleep apnea, and which treatments work best for different subgroups.

References

Carra, M. C., Huynh, N., & Lavigne, G. (2015). Sleep bruxism: A comprehensive overview for the dental clinician interested in sleep medicine. Dental Clinics of North America, 56(2), 387–413. https://doi.org/10.1016/j.cden.2012.01.003

Lavigne, G. J., Kato, T., Kolta, A., & Sessle, B. J. (2003). Neurobiological mechanisms involved in sleep bruxism. Critical Reviews in Oral Biology & Medicine, 14(1), 30–46. https://doi.org/10.1177/154411130301400104

Lobbezoo, F., Ahlberg, J., Raphael, K. G., et al. (2018). International consensus on the assessment of bruxism: Report of a work in progress. Journal of Oral Rehabilitation, 45(11), 837–844. https://doi.org/10.1111/joor.12663

Manfredini, D., Ahlberg, J., Aarab, G., et al. (2024). Towards a standardized tool for the assessment of bruxism: The Standardized Tool for the Assessment of Bruxism. Journal of Oral Rehabilitation, 51(1), 29–58. https://doi.org/10.1111/joor.13411

Minakuchi, H., Fujisawa, M., Abe, Y., et al. (2022). Managements of sleep bruxism in adult: A systematic review. Japanese Dental Science Review, 58, 124–136. https://doi.org/10.1016/j.jdsr.2022.02.004

Sakai, T., Kato, T., Yoshizawa, S., et al. (2017). Effect of clonazepam and clonidine on primary sleep bruxism: A double-blind, crossover, placebo-controlled trial. Journal of Sleep Research, 26(1), 73–83. https://doi.org/10.1111/jsr.12442

Zieliński, G., Pająk, A., & Wójcicki, M. (2024). Global prevalence of sleep bruxism and awake bruxism in pediatric and adult populations: A systematic review and meta-analysis. Journal of Clinical Medicine, 13(14), 4259. https://doi.org/10.3390/jcm13144259


Medical disclaimer
This article is for educational purposes only and is not intended to replace professional medical advice, diagnosis, or treatment. Speak with a qualified healthcare professional about questions or concerns related to your sleep. Read full medical disclaimer